


Orthodontics
Orthodontics
Indication and objective of orthodontic treatment
Orthodontics targets the desired alignment of teeth, dental arches and jaws in relation to one another and other anatomical structures according to aesthetic and functional concepts. All types of dysgnathia can be corrected, these include malocclusion of individual teeth (rotation, tipping, retention, elongation, malposition), malalignment of teeth in the dental arch (overcrowding, overlapping, diastemas), but also incorrect positioning of the maxilla and mandible to one another (occlusal anomalies).
Prophylaxis
Thumb-sucking and other habits are controlled or stopped and (also in interdisciplinary collaboration with other specialist disciplines such as logopaedics) swallowing or speech techniques are trained for example as prevention against malocclusion. Deciduous teeth should be preserved, if possible, or the spaces kept open (space maintainer) after loss of the deciduous teeth. Conversely, prophylactic extraction of teeth can also be practical.
Planning and documentation
In addition to clinical examination of the patient, mainly dental models and X-rays (orthopantomogram, OPM, OPG and lateral cephalometric radiograph LCR) are used in orthodontics for treatment planning and documentation of progress. Measurement in relation to reference points and lines are especially important for assessment.
Timing and duration of orthodontic treatment
In case of congenital anomalies, for example a lip-jaw-palate cleft, orthodontic treatment begins immediately after birth. With certain, highly pronounced and/or prognostically unfavourable malpositions early orthodontic treatments are indicated from age six onwards after eruption of the permanent incisors and first molars. The majority of treatments are performed during the juvenile growth phase before maximum puberty in the late mixed dentition between age nine and twelve. Corrections are also possible, however, with adult patients at any age, providing an alternative to other forms of dental treatments (e.g. dental restorations). The duration of treatment is measured in a minimum of months but generally a number of years may be required. To achieve planned treatment outcomes and prevent relapses retainers are fitted up to age 25 or 30 and sometimes also lifelong.
Forces and anchorage
Teeth are moved selectively by different types of biomechechanical forces (rotation, translation), which may be of natural (growth, movements, particularly in functional orthodontics, FO) or artificial origin. Mechanical appliances are often used as artificial sources of forces, e.g. resilient wires, compression and tension springs, elastics, expansion screws or plastic foils. In the balance between force and opposing force (actio = reactio) anchorage is always required, the stability of which must either be sufficiently predominant to remain practically unchanged or predictably moved in the opposite direction to the object of the movement. Other teeth or other groups of teeth can be used as anchorage as can alveolar bone or mini-implants inserted in the bone, as well as segments of the bony cranium (chin, forehead, back of the head). Forces in orthodontics must always be measured, so as to effect the required movement of teeth but without causing undesired side effects (e.g. resorption of the root cementum).
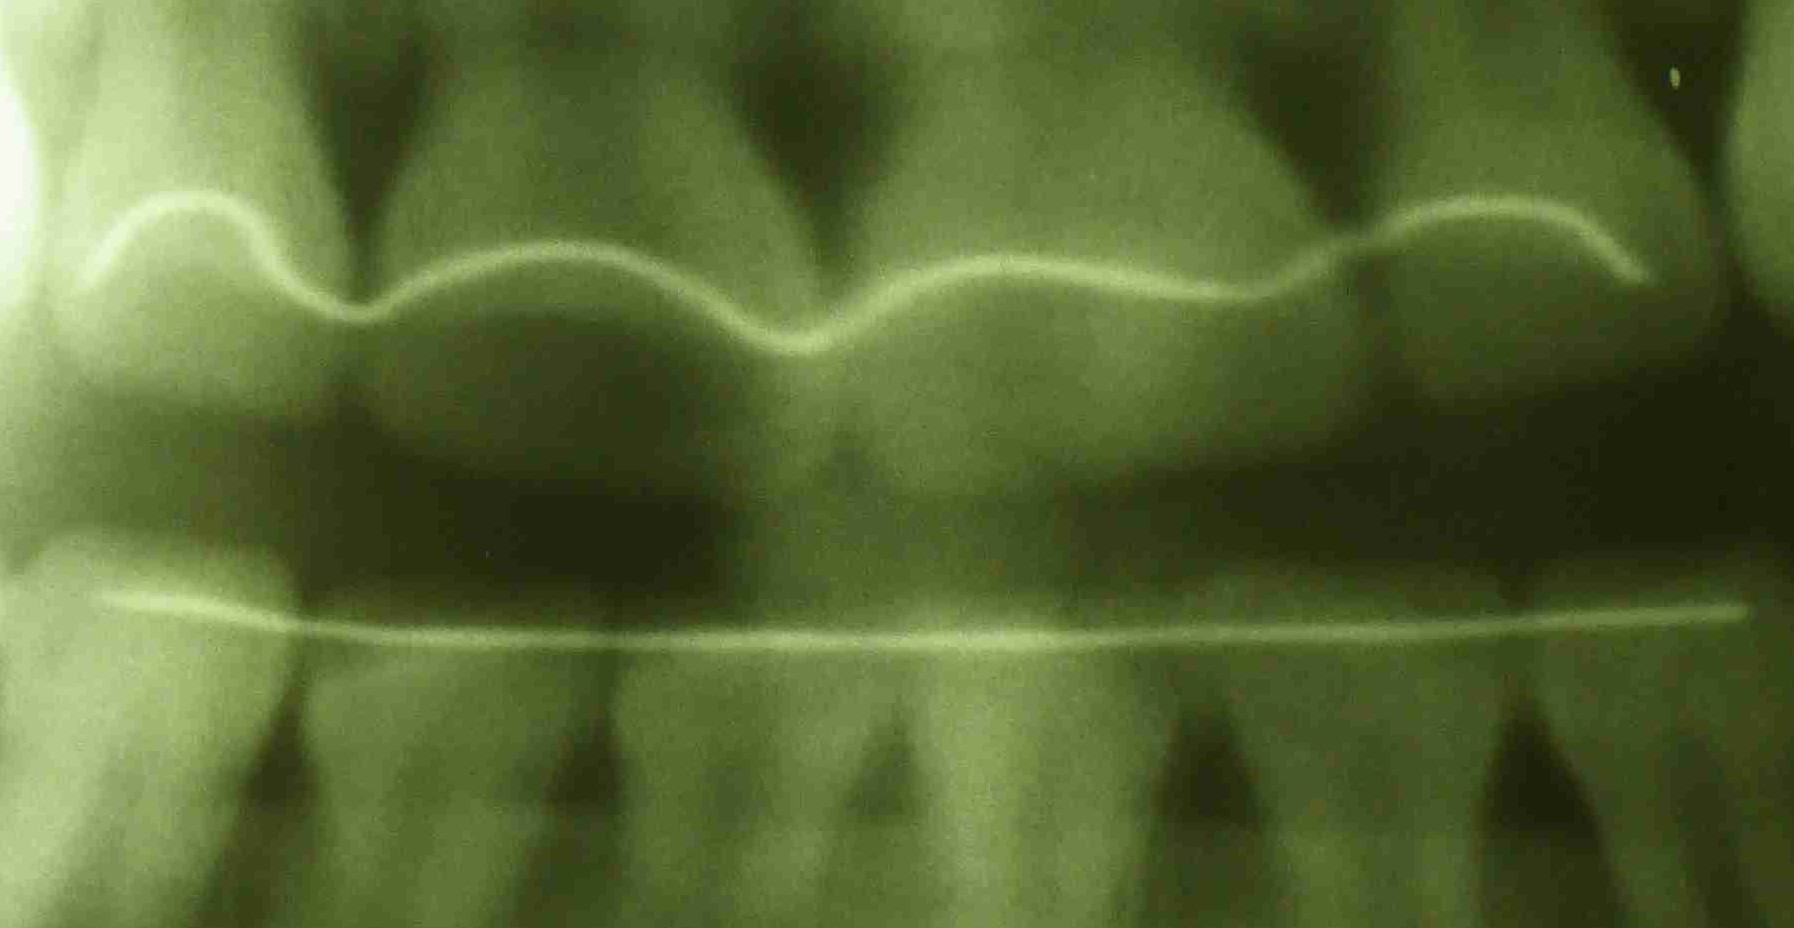 Upper and lower retentive bows (OPG)
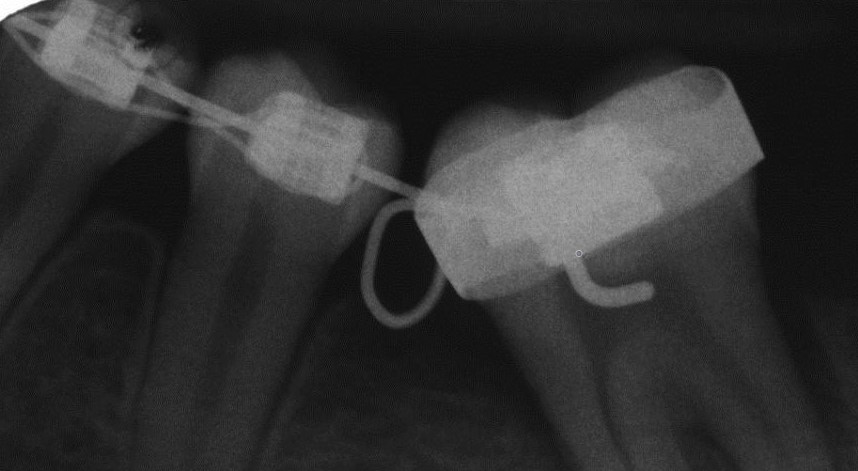 Brackets, molar band, ligatures (X-ray)
Appliances
Both fixed (e.g. brackets, bands, attachments, archwires) and removable appliances (e.g. activators and plates) are used in orthodontics. A differentiation is also made between extraoral (e.g. orthodontic facebows) and intraoral appliances. The latter can involve one or both jaws (bimaxillary appliances). Aesthetic orthodontics uses appliances that are as inconspicuous as possible, e.g. tooth-coloured archwires and brackets, transparent foils or lingual technique.
 Ceramic bracket with hook (© 3M)
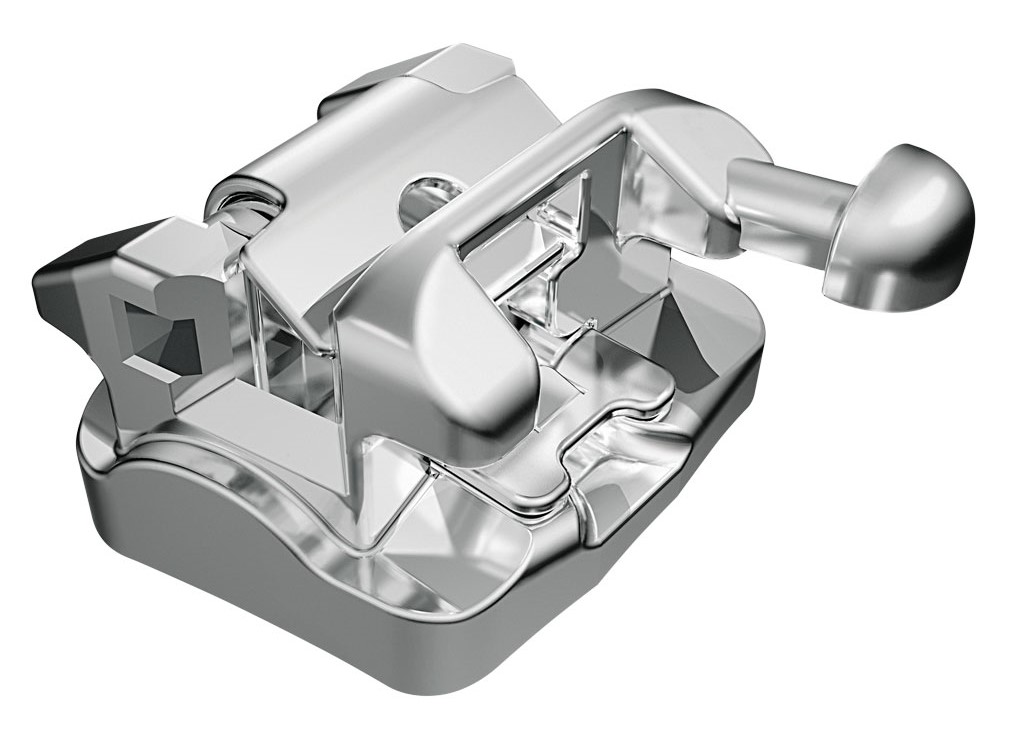 Self-ligating bracket (© FORESTADENT)
Surgery
Orthodontically indicated extraction of permanent teeth may also be required (extraction therapy) to remedy or prevent overcrowding. Serious malocclusions and anomalies of the jaw are also treated using orthodontic surgery, such as retention of permanent teeth using combined surgical-orthodontic procedures.
Want to give it a try ...
... or need professional advice?
Get in touch with us or click Contact.
Word of the day
| English | German |
|---|---|
| intraoral pin | Stützstift |
Focus text of the month
Impression materials …Impression materials Dental impression materials are used for taking impressions in the mouth. They are intended for reproducing and transferring the outer contours of intraoral structures (teeth, jaws, soft tissues, fillings, restorations) three-dimensionally during impression-taking. An initially soft material is applied directly to the surface, avoiding air voids where possible, before setting rapidly (between one and a few minutes) in a supporting impression tray to create a female mould (impression). The impression is then cast (usually with plaster but possibly with acrylic resin) to produce a model. In the past, plaster was used for taking impressions even though it was not elastic after setting. For this reason, a plaster impression of undercut structures (teeth) always had to be sectioned (fractured) in order to withdraw it from the mouth. Impression plaster was also used as a pick-up impression material for single-prep impressions taken using customised copper rings filled with thermoplastic (resin-based) impression material. However, after cooling and setting the rigid impression could not be removed from undercuts without being damaged. For this reason, nowadays rigid setting, reversible thermoplastic materials are only used in non-undercut regions, e.g., resins for functional impressions on denture peripheries or waxes for bite registration. Special zinc-oxide-eugenol impression materials may also be used when taking functional impressions. For decades almost only impression materials which remain elastic after setting and, when sufficiently thick, virtually fully recover their original shape after removal from the mouth, have been in use. This property is referred to as “elastic recovery”. These include alginate impression materials which, when mixed with water, form gel-like polysaccharides. As alginate impressions may dry out or absorb further water and swell, they are neither dimensionally stable nor can they be stored for longer periods. This also applies to reversible hydrocolloids. In the meantime, so-called elastomeric alginates, which are generally irreversible materials and set to a rubbery-elastic consistency, are widely accepted. The chemistry behind the chain reactions can be divided into polymerization (e.g. polyether impression materials), polyaddition (e.g. A-silicones) and polycondensation (e.g. C-silicones, polysulfides). These impression materials are either mixed by hand or mechanically (refer to “Mixing systems for impression materials”) to combine two components (“base” and “catalyst”) homogeneously and void-free.
Silicone impression materials (polyvinyl siloxanes, PVS) in particular are supplied in different consistencies for various impression procedures. When taking one-step or two-step putty-wash impressions, a kneadable (heavy body) putty exerts controlled pressure (usually in an impression tray) on a syringeable, light body, low viscosity precision impression material. This allows it to penetrate narrow gaps (e.g., intraorally in the gingival sulcus, interdental spaces, fissures) thus increasing the accuracy of detail (crispness) of the precision impression. Materials which are also kneadable yet slightly less viscous, and with an extended setting time, are used for taking functional impressions for full dentures. They intentionally displace very compressible mucosal areas more than firm sections (varying mucosal resilience) thus balancing the pressure exerted which reduces the risk of denture sores. Regular body silicone impression materials are either used with other materials or alone (monophase) e.g., for taking pick-up impressions for fixed/removable restorations either involving implants or not.
To ensure that the impression material flows smoothly onto surfaces, which are often moist, a degree of hydrophilicity (acute contact angle) is desirable. The setting reaction of impression materials may be accelerated by specific additives or a warmer environment (e.g., intraoral) but can also be retarded by inhibitors or precooling. Processing encompasses the mixing time, working time (loading the tray with impression material and inserting it into the mouth) and setting time. Special chromatic impression materials change colour to indicate the changes. Silicone impression materials which attain their final hardness very quickly can also be used for bite registration. Nowadays, materials for analogue impressions are often no longer required as contactless optical procedures using intraoral scanners are increasingly in use (digital impression-taking). |
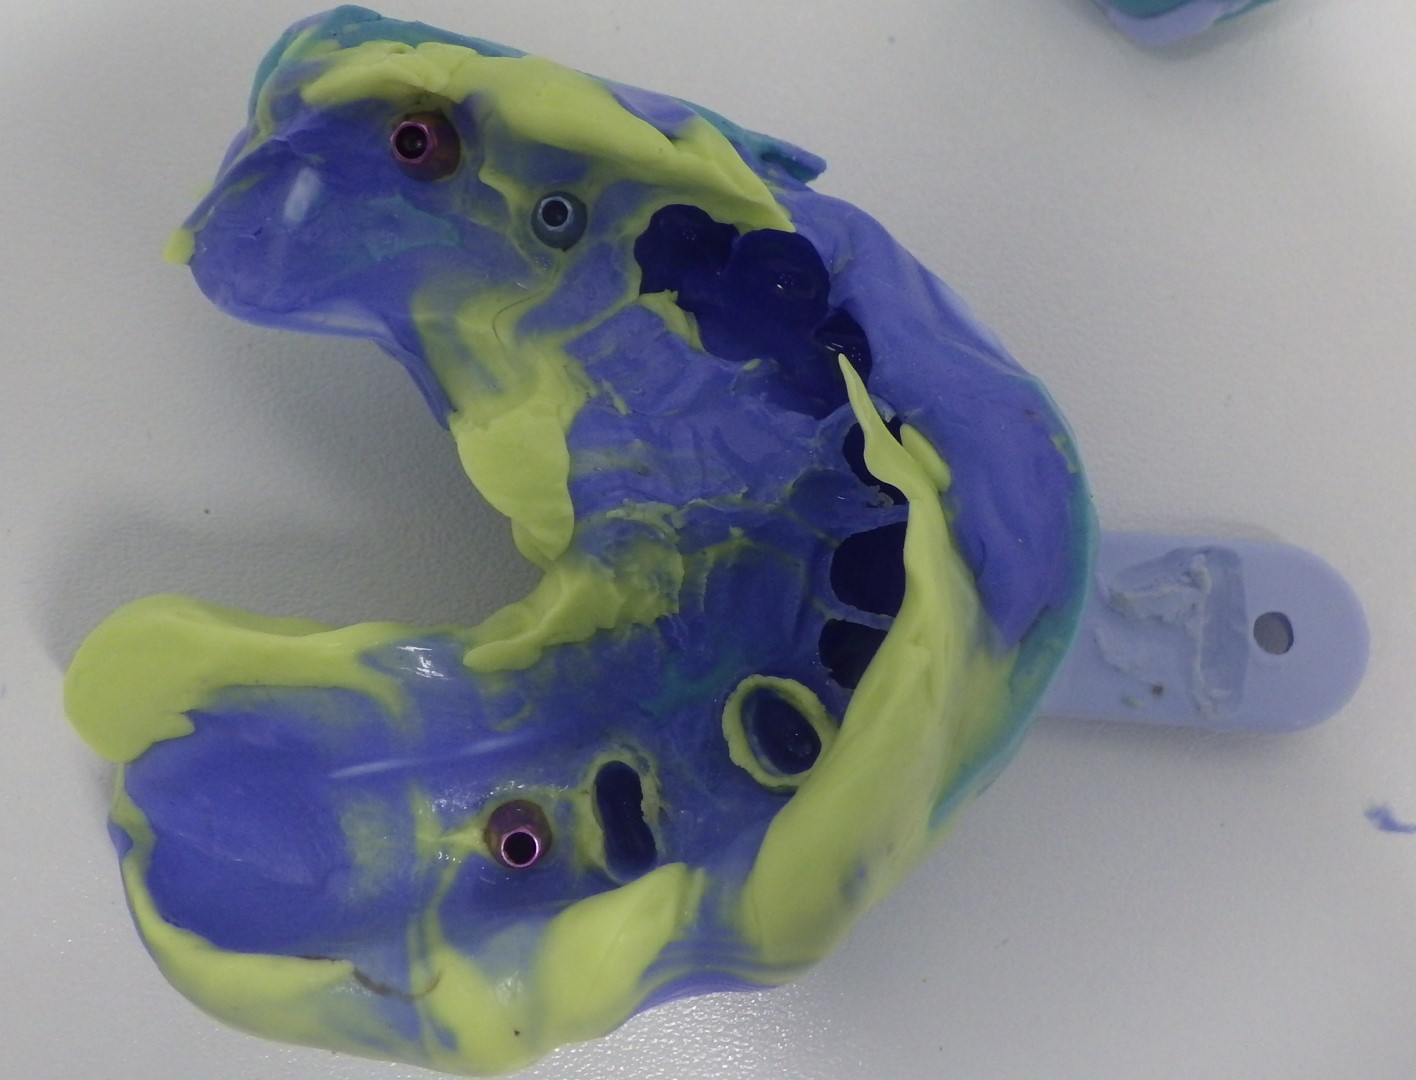 One-step putty-wash impression taken with regular and light body silicones over impression posts
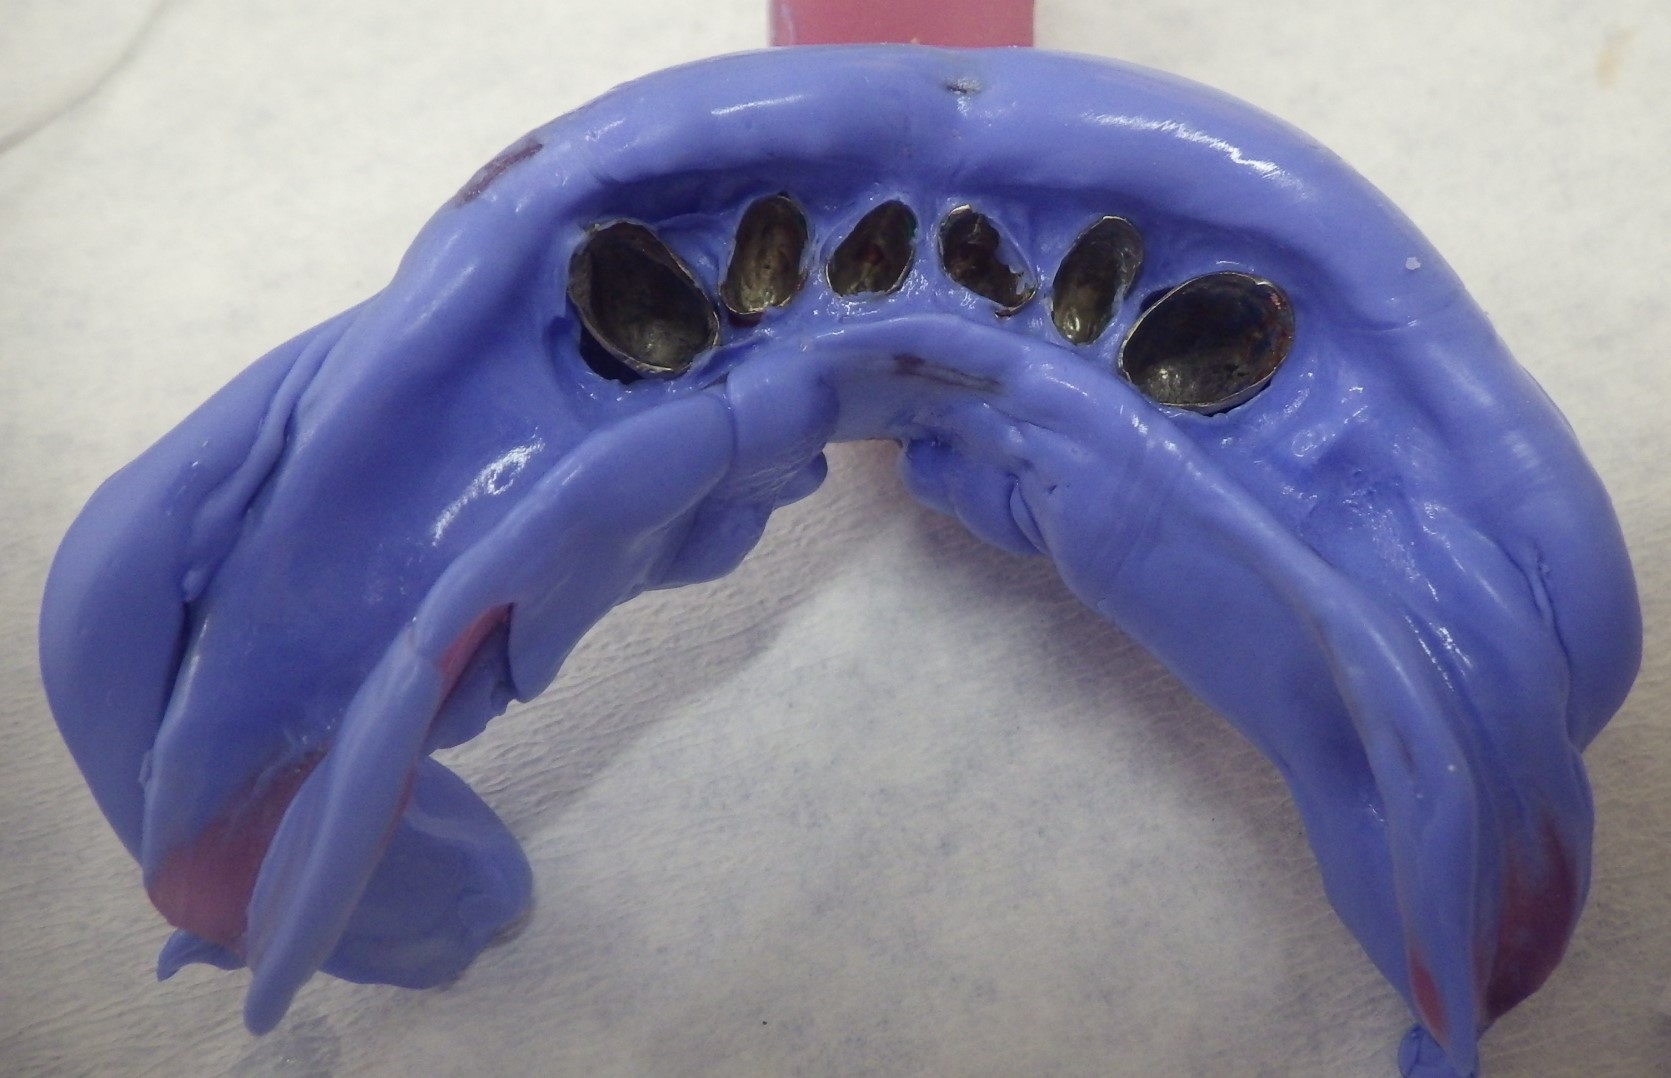 Pick-up impression taken over inner telescopes using monophase silicone